





Some Sunset Pictures I Took While in Buffalo 🌞🌻☀️
Please excuse my effusiveness, but it is appropriate to the occasion! I have been invited to blog for International Bipolar Foundation (IBPF) by its founder Ms. Muffy Walker. Thrilled and excited about this development. Of course, I’ll post my blog posts from IBPF here on my blog 🙂

 Mental illness, it’s invisible. There are no bandages, no casts, no crutches, no external wounds. How do you know someone is suffering from one? We, the afflicted, talk about feeling bad, talk about our depression and anxiety woes. You, our friends, look at us with bewildered eyes. You think to yourself “This person is all put together, she has makeup on, is dressed well, there are no signs of illness. I don’t understand.”
It’s not easy to explain mental illness to people who don’t have it. You can’t show them anything that is broken, or any flulike symptoms, or anything visible at all.
The key is listening, trying to understand where your mentally ill friend is coming from, what your mentally ill friend feels like, what they are trying to explain to you. And many will not even explain anything, because of the stigma, because they don’t want to appear “crazy” or abnormal.
Yes it’s confusing. I’ve had bipolar disorder since 1985, and sometimes it’s still confusing for me, so don’t anyone beat themselves over this. Basically the only empirical thing you have to gauge mental illness by is behavior. For example, in mania, people talk a lot, have very high energy, don’t sleep much, may have delusions of grandeur, may have a lot of anxiety. In depression, they have no energy, may sleep a lot, or not, are in a downcast mood, hopeless, and may also have a lot of anxiety. Paradoxically, in hypomania (the stage before going into full blown mania), we can actually get a lot accomplished, we are energetic, focused, not over the edge yet. This might be considered the “industrious” phase of bipolar disorder.
So the way your friend is behaving, a departure from their normal self, is a clue to their mental illness. What they are saying and how they’re saying it is as well. Are they being grandiose, talking non stop, switching from subject to subject (flight of ideas,) these are all clues.
In schizophrenia, people can have auditory hallucinations, where they hear voices, that’s definitely a clue, if they tell you, if they are aware that this is happening and admit to it… Yet most of the time, looking at a mentally ill person, you’d never know anything was wrong at all. It’s all below the surface, in their brain. Just like in a sea, where the water looks still and calm but a savage riptide is flowing under the surface.
Signs and signals, feelings and observations, those are clues to understanding mental illness. Just being an observant and understanding friend who listens and tries to comprehend what is being said and shown to them, that my friends is what is needed to understand the illusive nature of mental illness.
Two words: Medial Amygdala and Acetyl Carnitine… ok that’s 5 words, but it’s still two concepts 🙂
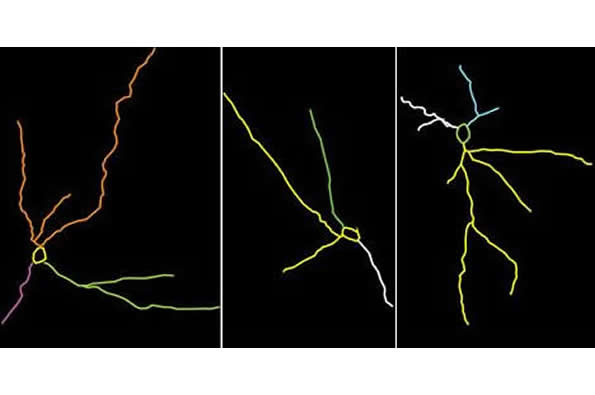
Chronic stress can make us worn-out, anxious, depressed—in fact, it can change the architecture of the brain. New research at The Rockefeller University shows that when mice experience prolonged stress, structural changes occur within a little-studied region of their amygdala, a part of the brain that regulates basic emotions, such as fear and anxiety. These changes are linked to behaviors associated with anxiety and depressive disorders
There is good news, too: an experimental new drug might prevent these changes.
“There have been hints that the amygdala displays a complex response to stress,” says lead author Carla Nasca, a postdoc in Bruce S. McEwen’s lab. “When we took a closer look at three regions within it, we found that neurons within one, the medial amygdala, retract as a result of chronic stress.
“While this rewiring can contribute to disorders such as anxiety and depression, our experiments with mice showed that the neurological and behavioral effects of stress can be prevented with treatment by a promising potential antidepressant that acts rapidly,” Nasca says.
In the research, published in Molecular Psychiatry, her team found this protective approach increased resilience among mice most at risk for developing anxiety or depression-like behaviors.
The brain’s limbic system controls emotions and memory, and it comprises a number of structures, including the amygdala, which is found deep in the brain. Scientists interested in the neurological effects of stress have focused on several structures in the limbic system, but the medial amygdala has thus far received little attention in stress studies.
To see what was going on in this area, as well as two other parts of the amygdala, Nasca and her team first subjected mice to 21 days of periodic confinement within a small space–an unpleasant experience for mice. Afterward, they tested the mice to see if their behaviors had changed–for instance, if they had begun to avoid social interaction and showed other signs of depression. They also analyzed the neurons of these mice within the three regions of the amygdala.
One area saw no change with stress. In another, the basolateral amygdala, they saw that neurons’ branches became longer and more complex—a healthy sign of flexibility and adaptation, and something that had been shown up in previous work. But in the medial amygdala, the neuronal branches, which form crucial connections to other parts of the brain, appeared to shrink. The loss of connections like these can harm the brain, distorting its ability to adapt to new experiences, leaving it trapped in a state of anxiety or depression.
This effect could be prevented. The scientists repeated the stress experiment, and this time they treated mice nearing the end of their 21 days of chronic stress with acetyl carnitine, a molecule Nasca is studying for its potential as a rapid-acting antidepressant. These mice fared better than their untreated counterparts; not only were they more sociable, the neurons of their medial amygdalas also showed more branching.
Stress does not affect everyone the same way. This is true for both humans and mice—some individuals are just more vulnerable. Nasca and her colleagues’ experiments included mice at high risk of developing anxiety- and depression-like behaviors in response to stress. Treatment with acetyl carnitine also appeared to protect these mice, suggesting that a similar preventative approach might work for depression-prone people.
Both humans and rodents naturally produce acetyl carnitine under normal conditions and several depression-prone animal models are deficient in acetyl carnitine. In a separate study, Nasca and colleagues are examining whether people with depression have abnormally low levels of the molecule.
“Chronic stress is linked to a number of psychiatric conditions, and this research may offer some new insights on their pathology,” McEwen says. “It seems possible that the contrasting responses we see within the amygdala, and the limbic system in general, may contribute to these disorders’ differing symptoms, which can range from avoiding social contact to experiencing vivid flashbacks.”

When we feel physical pain, we have no qualms about going to a doctor and getting it looked at and treated. For example, if we break an arm, there is no hesitation at all in going to see an orthopedist, getting it x-rayed and putting a cast on it, no hesitation in taking pain relievers to stop your arm from hurting. No negative self talk or blame, we don’t say things like “You are an idiot, your are so weak, you can never do anything right, you broke your arm out of sheer incompetence.”
But when we feel psychological pain, we don’t ask for help. We deny it. We try to do other things, like watching TV, reading a book, or even self medicating, rather than going to see a professional about it. Why is that? Why is it harder to simply take the psychological pain at face value and get help?
Well for one, you can’t see psychological pain, you can’t take an x-ray of it like you can of your broken arm and know that something’s wrong. Also, a broken bone is a broken bone, but each person’s depression can have different symptoms, or present in different ways. Psychological pain is more nebulous. Not only do other people have trouble believing that you are suffering, but you yourself doubt there’s really anything wrong. One minute you feel awful, the next minute you’re feeling better. And of course, there is a lot of negative self talk, you are a loser, you will never amount to anything, it’s all in your head, come on just snap out of it and on and on and on. And then, because you don’t want to admit to anyone else that you aren’t feeling well, there is the self medication, the distracting methods like TV, pretending to be fine with happy people, etc. etc.
Well, what if when you didn’t feel good psychologically, you did take yourself seriously, what if you didn’t run away from or try to mask your feelings? I know this is painful, to face the pain! It’s not for nothing that it is called psychological pain! But facing your pain, even though it is uncomfortable, even though you are afraid, what if you went for help to a psychologist or psychiatrist and examined those painful feelings or talked about the issues and even got some appropriate medication? What if you didn’t engage in negative self talk, self abusive talk?
Yes the problem may be more nebulous, but you know when you don’t feel well. Perhaps mental illness runs in your family, what if you accept you are feeling unwell, and be compassionate with yourself and get help from a professional.
Yes these issues are nebulous, and things like “inner child” work is non specific, but these things really work. Medication, even if you have to try a few, really works. All these modalities can only help you.
We must be as motivated to ensure that we feel better from psychological pain as we are to feel better from physical pain.
The brain is the most complicated organ in the body. So when you have a disease of the brain, which is what a mental illness is, it is more difficult to gain an understanding of what is going on than in our example of the broken arm. Certainly there are complicated physical illnesses such as cancer, but any neurological or mental illness in general is very (even the most) complicated and difficult to understand and treat.
Knowing this, knowing we are dealing with a complicated illness, and we as people with mental illness are also trying to understand our illness with the same organ that is suffering from the illness, namely the brain, we can approach mental health professionals, experienced people in treating mental illness and make sure we get help and treatment.
What if we can say to ourselves that we have an illness of the brain. The brain is a physical organ, so as far as I’m concerned, there is no such distinction as psychological pain vs physical pain. It is all pain due to one organ (eg. brain, pancreas) or body part (eg. broken arm) or other. Can we not get past that psychological vs physical dichotomy? If we could, we would then say “Oh, I am not feeling well, I am experiencing psychological pain, I need to see a doctor who specializes in treating such illnesses of the brain.” And we would get treated without stigma, without beating ourselves up, and we would get better and feel better. Amen!

This is my grandmother’s solid silver tea set that was passed on to my mother and then to me! When it’s polished, it looks absolutely beautiful, but I like it like this too. My grandmother got married in 1926, and must have gotten this as one of the pieces in her dowry.

This is a newspaper that came out of the walls of our 110 year old condominium in Louisville, we were doing a major renovation. It’s from 1937! Quite a surprising find!
https://hughsviewsandnews.com/2016/05/31/hughs-weekly-photo-challenge-week-27-vintage/
I know, we’ve heard all or most of these before, yet this is so spot on that I decided to post it. One more thing I would add is to give up expectations, giving up expecting other people to act a certain way will definitely contribute to our happiness, because we all act our own way, not the way that someone might expect us to act. That is normal and should be the expectation. Ok time for me to go off to dreamland. So good night my friends 😴💤
Wow, this is quite amazing. Diabetic people who get bariatric surgery don’t need to be on insulin anymore. This is more than just the effect of the following weight loss. Changes to GI anatomy can directly influence glucose homeostasis! Quite amazing. GI surgery can cure diabetes!
Wouldn’t it be wonderful if they found knee replacement operations cured bipolar disorder 🙃🙃
http://www.nature.com/news/medical-research-time-to-think-differently-about-diabetes-1.19955?WT.mc_id=FBK_NatureNewsClinical guidelines published this week1 announce what may be the most radical change in the treatment of type 2 diabetes for almost a century. Appearing in Diabetes Care, a journal of the American Diabetes Association, and endorsed by 45 professional societies around the world, the guidelines propose that surgery involving the manipulation of the stomach or intestine be considered as a standard treatment option for appropriate candidates. This development follows multiple clinical trials showing that gastrointestinal surgery can improve blood-sugar levels more effectively than any lifestyle or pharmaceutical intervention, and even lead to long-term remission of the diseases.
As someone who has been investigating the link between gastrointestinal surgery and glucose homeostasis since the late 1990s (see ‘Surgical breakthrough’), I have witnessed first-hand how getting to this point has required many clinical scientists to put aside long-standing preconceptions. Indeed, the guidelines come nearly 100 years after the first clinical observations that diabetes could be improved or even resolved by a surgical operation (see ‘A long road’)2. The evidence that surgery can prompt the remission of a disease that has long been considered irreversible could bolster searches for what causes diabetes and even reinvigorate hopes to find a cure. But future progress will require more thinking outside the box.
Surgical breakthrough
In 1925, a report in The Lancet2 described a ‘side effect’ of a gastrointestinal operation to treat a peptic ulcer. This was the almost overnight resolution of an excess of sugar in the urine (glycosuria) — the chief symptom of diabetes at the time. Similar observations were reported in subsequent decades and became more common after the advent of bariatric or weight-loss surgery in the mid 1950s, which led to more people with diabetes receiving these types of operations. And during the 1980s and 1990s, resolution of diabetes after bariatric surgery was noted on many occasions, including in a landmark report involving more than 120 patients9.
In 1999, while working as a research fellow at Mount Sinai School of Medicine in New York City, I stumbled across a report showing that nearly all people with type 2 diabetes who had undergone a complex bariatric operation (biliopancreatic diversion) had completely normal blood-sugar levels as early as one month after surgery. They had been able to stop taking medication and come off a low-calorie diet. I wondered whether gastrointestinal surgery could influence diabetes directly. If so, surgery could be used to treat diabetes or to understand how it works.
The next day, I persuaded my mentor to seek approval from the institutional review board to run trials in humans. Failing to obtain approval, we turned to rats to investigate whether a modified form of gastric-bypass surgery could directly influence glucose homeostasis. Our experiments confirmed that it could, although it took us more than two years to publish the findings.
In 2006 and 2007, surgical teams showed that the operation had the same effect in humans, and other groups began to investigate the molecular mechanisms that might be responsible. On the back of these studies, a multidisciplinary group of leading clinicians and scientists at the first Diabetes Surgery Summit in 2007 reviewed the preliminary mechanistic and clinical data available on the effects of surgery on diabetes and established an agenda for research priorities. The summit inspired the randomized clinical trials that now provide the evidence supporting a role of surgery in diabetes. In September 2015, the introduction of surgery into standard care for type 2 diabetes was formally recommended by the participants of the second Diabetes Surgery Summit.
Clinical shift
The number of adults around the world with diabetes quadrupled from 108 million in 1980 to 422 million in 2014 (ref. 3). About 90% of these people have type 2 diabetes — a major cause of kidney failure, blindness, nerve damage, amputations, heart attack and stroke. Fewer than 50% of people with type 2 diabetes control their blood-sugar levels adequately by changing their diet or exercise regime, or by taking drugs.
Bariatric or weight-loss surgery refers to various procedures. Surgeons may, for instance, remove a portion of the person’s stomach or divide the stomach into two and reroute the small intestine to the upper part (see ‘Gastric bypass’). Since the mid 1950s, people whose body mass index (BMI) is greater than 40 have received bariatric surgery to induce weight loss. Many of these people also had diabetes. The new guidelines advise that such procedures (metabolic surgery) be considered specifically for the treatment of diabetes in people who have not adequately controlled their blood-sugar levels through other means, and whose BMI is greater than 30 (or 27.5 for people of Asian descent). Perhaps more significantly, they also state that the gastrointestinal tract is an appropriate biological target for interventions designed to treat diabetes.
These recommendations arguably signify the most radical departure from mainstream approaches to the management of diabetes since the introduction of insulin in the 1920s. They are based on findings from a large body of work, including 11 randomized clinical trials conducted over the past decade1. In these studies, most surgically treated people (up to 80% in a recent 5-year follow-up4 of a randomized trial) fall into one of two categories. Either their diabetes goes into apparent remission or their blood-sugar levels can be stabilized using reduced medication or exercise and a calorie-controlled diet (see ‘Big benefits’).
Non-randomized studies, involving people receiving surgery and matched subjects treated with standard interventions, suggest that surgery may also reduce heart attacks, stroke and diabetes-related mortality1. And several economic analyses suggest that the costs of surgery (roughly US$20,000–25,000 per procedure in the United States) may be recouped within 2 years through reduced spending on medication and care.
I’m still in Buffalo, spending really wonderful days with my son. I am so happy that I am able to do this. We’ve had a graduation, parties, and dinners, and the Stanley Cup Playoffs, and movies and shooting bows and arrows, and wonderful conversations and meals. And I know I am one lucky mom because I have such a great relationship with my son!
But this Friday, I’ll be going back to Louisville, and that’s where the “but” comes in. That’s when I know I’ll look at all these pictures and miss my son very much and fear that something may go wrong and miss him, miss him, and miss him some more. Ugh… is that what being a mother means, or are my emotions more extreme because of bipolar disorder? I know some moms who miss their children just as much as I do and they don’t have even one symptom of bipolar disorder. I think it is just being a mom, you give birth to these helpless little infants. You heart just breaks seeing how little and adorable they are, you take care of them and love them unconditionally, your primary role is mother, at least for 18 years. Then they leave for college and your heart breaks for the absence of them. Of course you’re happy they’re on their way to an independent life, you wouldn’t have it any other way, but… and here’s that but again. But, as happy as you are that your babies are growing up, your heart breaks that you are not a family anymore, that you are no longer a hands on mom, and you miss your children no matter how old and accomplished they get, you just miss them.
Well, I’m telling myself right now to start preparing for the low next week, but also to remember I will most likely be back in July 🙂 so it won’t be too much of a low. And writing this out helps, because it reminds me that nothing is as bad as my mind sometimes makes it out to be. Writing therapy! Also why writing a journal is exceptionally helpful. Here’s to all the moms out there who love their children, may we be loving, happy, and healthy, and so may our wonderful children!








Sometimes I think I am guilty of a few of these biases. This is a good article because if you can be aware that you are thinking in some of these paranoid ways, then you can tell yourself to stop. Or at least try. Knowledge is power!
In everyday language, the term paranoia refers to someone who feels excessively suspicious without justification, and/or that others are plotting against him. They read far too much into everything people say and are quick to criticize, but they are not open to criticism themselves. The term “mountains out of molehills” aptly describes paranoid individuals. Research indicates that many of us, perhaps 15 to 30 percent, will regularly experience suspicious thoughts. For example, about 42 percent of college students reported that at least once a week others were spreading negative comments about them. The overall emotional state of a person who is paranoid is a negative one (depressed mood, anxiety, and lowered self-esteem).
Paranoia is disorder of mind, not a flaw of character. Paranoid individuals tend to have false ideas about the world and people. Here is a 8 such biases that prevent them being rational:
1. Confirmation bias.
A suspicious person is a person who has something on his mind, and searches intensely for confirmation of his anticipations. He will pay no attention to rational arguments except to find in them some aspect or feature that confirms his original view.
2. Attention bias.
The instrument for an individual’s confirmation bias is his attention. His attention is intense and exceedingly narrow in focus. For example, a person with low self-esteem is highly sensitive to other people ignoring them. They constantly monitor for signs that people might not like them.
3. Disorders of reasoning.
Once a suspicious person accepts a belief based on some evidence, he is reluctant to give it up. When hearing new evidence, he is less likely to revise his original judgments about the possibility of alternative explanations.
4. Distorted reality.
The paranoid person imposes a biased view on the actual world. Their thought processes go from belief to evidence. A paranoid person generally listens and watches only for specific clues that interest him, which tie into suspicious beliefs. For instance, in a conversation with a coworker, he overlooks nuances and misses the true intent as he fails to read between the lines, instead focusing on what he wants to see.
5. Persecutory delusion.
They are blaming individuals and they explain life events by blaming others. For example, they explain negative events (e.g., losing a job) by attributing them to the malicious intentions of others rather than worrying about whether they are inadequate in some way. (The flip side of persecutory delusion is grandiosity, which serves to defend against anxieties and vulnerabilities. In an attempt to cope with low self-esteem and the fear of that no one loves them, they convince themselves that everyone does.)
6. Paranoid projection.
Projection is the substitution of an external threat or tension for an internal one that one’s self denies. For example, “I hate him” becomes “He hates me.” This mental operation is central to paranoid thought. For example, a paranoid person who has made a small mistake on the job will search for clues of disapproval (or dislike) in his boss’s behavior. When he finds that sign, the biased anticipation becomes a conviction of disapproval.
7. Overvalued ideas.
An overvalued idea is a simple idea that resembles a delusion, and often guides specific behavior. An example is knocking on wood to protect yourself against misfortune. Many people endorse the “10-second rule” that says you can eat food that has fallen on the ground only if you pick it up immediately. One aspect of superstition is the idea of magical thinking—that you have control over the world. Many hotels don’t have a thirteen floor. But what could happen to a guest on the 13th floor that would not occur on the 14th floor?
8. Erroneous sense-making.
The suspicious person can be absolutely right in his perception and at the same time absolutely wrong in his judgment. Making sense is a deep human motivation, but it is not the same as being correct. Michael Gazzaniga (2008) argues that the pressure to justify one’s actions reflects the operation of “an interpreter system” in the left-hemisphere (analytical) brain. The interpreter (the “I”) is driven to generate explanations and hypotheses regardless of circumstances. In other words, the brain only perceives what it wishes to. As Mark Twain remarked, “What gets us into trouble is not what we don’t know, it’s what we know for sure that just ain’t so.”

